Untreated White Coat Hypertension Linked to Increased CV Risk
白袍高血壓不是像一般想像的,是良性而不用治療。
根據Annals of Internal Medicine一篇meta analysis,收入64,000案例,追蹤3到19年,發現:
“沒有治療的白袍高血壓相較於正常血壓者有增加33%的死亡率。但是,若是有治療的白袍高血壓患者,則沒有死亡率增加的情況。〝
白袍高血壓沒有治療者:
- increased risk for cardiovascular events (hazard ratio [HR], 1.36 [95% CI, 1.03 to 2.00])
- all-cause mortality (HR, 1.33 [CI, 1.07 to 1.67]),
- cardiovascular mortality (HR, 2.09 [CI, 1.23 to 4.48])
白袍高血壓有治療者(WCE):
- No significant association was found between treated WCE and cardiovascular events (HR, 1.12 [CI, 0.91 to 1.39]), all-cause mortality (HR, 1.11 [CI, 0.89 to 1.46]), or cardiovascular mortality (HR, 1.04 [CI, 0.65 to 1.66]).
REVIEWS |11 JUNE 2019
Cardiovascular Events and Mortality in White Coat Hypertension: A Systematic Review and Meta-analysis
https://annals.org/aim/article-abstract/2735719/cardiovascular-events-mortality-white-coat-hypertension-systematic-review-meta-analysis
2019年6月13日 星期四


2019年5月25日 星期六
大陸腎友來台參加法會、丙肝、乙肝、B肝、C肝
今天一位北京的腎友來高雄參加法會,經由社團法人台灣腎友生活品質促進協會轉介來本診所透析,因為翻譯醫學名詞的關係,大陸使用乙肝(就是台灣稱的B肝、B型肝炎)、丙肝(C肝、C型肝炎),在口語聽覺上「丙肝」和「B肝」非常相似,要注意不要弄錯型別,因為這是和透析患者肝炎分區有相關性的。除了肝炎外,一些常見的檢驗值單位也和台灣不同,例如鈣 (台灣用 mg/dL)大陸用(mmol/L)和血色素 (台灣用 g/dL)(大陸稱血紅蛋白,單位是 g/L)。


腎友能走出來,二岸能交流是一件好事!
#TravelDialysis
2019年4月24日 星期三
沒吃早餐和心血管死亡率有關係?
Association of Skipping Breakfast With Cardiovascular and All-Cause Mortality
Journal of the American College of Cardiology
Volume 73, Issue 16, April 2019
DOI: 10.1016/j.jacc.2019.01.065
很少文章提到不吃早餐和心血管疾病的相關性,因此這標題吸引了我:
METHODS
Prospective cohort study
6,550 adults 40 to 75 years of age
17 to 23 years of follow-up
RESULTS
5.1% never consumed breakfast
10.9% rarely
25.0% some days
59.0% every day
Adjustment for age, sex, race/ethnicity, socioeconomic status, dietary and lifestyle factors, body mass index, and cardiovascular risk factors,
participants who never consumed breakfast compared with those consuming breakfast every day had hazard ratios of 1.87 (95% confidence interval: 1.14 to 3.04) for cardiovascular mortality and 1.19 (95% confidence interval: 0.99 to 1.42) for all-cause mortality.
CONCLUSIONS
Our study supports the benefits of eating breakfast in promoting cardiovascular health.
---
因此早餐一定要吃,對心血管健康有幫忙。
Journal of the American College of Cardiology
Volume 73, Issue 16, April 2019
DOI: 10.1016/j.jacc.2019.01.065
很少文章提到不吃早餐和心血管疾病的相關性,因此這標題吸引了我:
METHODS
Prospective cohort study
6,550 adults 40 to 75 years of age
17 to 23 years of follow-up
RESULTS
5.1% never consumed breakfast
10.9% rarely
25.0% some days
59.0% every day
Adjustment for age, sex, race/ethnicity, socioeconomic status, dietary and lifestyle factors, body mass index, and cardiovascular risk factors,
participants who never consumed breakfast compared with those consuming breakfast every day had hazard ratios of 1.87 (95% confidence interval: 1.14 to 3.04) for cardiovascular mortality and 1.19 (95% confidence interval: 0.99 to 1.42) for all-cause mortality.
CONCLUSIONS
Our study supports the benefits of eating breakfast in promoting cardiovascular health.
---
因此早餐一定要吃,對心血管健康有幫忙。
2019年4月13日 星期六
不反對即同意捐出器官的德國
全世界器官衰竭的病人,缺可移植的器官可用是普遍的,德國2019年4月1日,史班與其他國會議員一起提出了草案
新器捐草案:雙重反對制
其中與器官捐贈登錄相關的最核心要點如下:
1. 年滿16歲者,應至少3度得到器官捐贈相關的充分資訊,以充分思考自己如何表達意願;一年後,除非明確表達反對意願,否則即被視為器官捐贈者。反對意願必須被明確登錄在聯邦資料庫中,但當事人可隨時更改甚至取消。
2. 器官捐贈者也必須被登錄在資料庫中。
3. 倘有疑慮,當事人的家屬可在明確提出「當事人不願成為捐贈者」證據的前提下,代為決定。
如果這個法案通過,未來器官捐贈的流程將更改為:在一位成年公民死亡後,醫師將會檢查聯邦資料庫內是否登錄了死者的反對意願,如果沒有,醫師必須徵詢死者家屬,死者生前是否有任何明確的書面反對意願,或有其他形式證據,證明死者不願成為器官捐贈者。此外,除非死者生前明確授權,家屬沒有為死者決定的權利。
這個制度被稱為「雙重反對方案」(doppelte Widerspruchslösung),也就是說,必須確認死者有無登錄資料庫,以及有無向家屬明確表示其意願。在完全找不出反對意願下,死者即成為器官捐贈者。
然而,也有反對的聲音
反對修法的理由:侵犯個人自主權
史班的思考方式,引來許多反對意見。例如自由民主黨黨魁林德納(Christian Lindner)便表示:他是器官捐贈的支持者,但史班的提案是對個人自主權利的侵害。沉默,不應該被視為同意。
這個批評點出了支持與反對方最大的爭執:為什麼不能有沉默的權利?為什麼沉默者,必須被視為同意?
神學家及全國倫理委員會(Deutscher Ethikrat)主席達布羅克(Peter Dabrock)質疑:「沉默即同意」的邏輯,忽視了有些人的心智狀態根本無法處理器捐議題所需資訊,亦無法做出重要決定,而這樣的「沉默」者,其身體卻會自動被國家徵用。
https://www.twreporter.org/a/opinion-germany-organ-donation
https://www.zeit.de/wissen/gesundheit/2018-09/widerspruchsloesung-jens-spahn-organspende-neuregelung
默認捐贈(Opt-out)VS 自願捐贈(Opt-in)
香港現時採用「自願捐贈」(Opt-in) 模式,有意在身故後捐出器官的市民,需要事先登記,以表明身故後捐贈器官的意願。環顧大部分東南亞國家,除新加坡外,還有加拿大、美國、英國、澳洲都採用這方式。
歐洲國家則大多採用「默認捐贈」(Opt-out) 模式,政府假設所有民眾都在同意身故後捐出器官,不同意者需以書面形式提出「不捐贈」意願,但最終會否捐贈器官則會尊重家屬的決定。目前全球至少有超過20個國家或地區採用「默認捐贈」模式,包括西班牙、瑞士、法國、意大利、比利時及新加坡等。
但「默認捐贈」不是萬靈丹,並非所有採用這方法的國家有很高的器官捐贈率。希臘,盧森堡和斯洛伐克都是「默認捐贈」,但器官捐贈率比「自願捐贈」的加拿大低。連西班牙國立移植組織(Spanish National Transplant Organisation)主席亦曾明言「默認捐贈並不是提升捐助率的主要因素」。瑪麗醫院器官移植聯絡主任古慧敏認為,完善的溝通網絡及通報機制、由醫生負責向死者家屬提出及解釋器官捐贈、醫療體系將器官捐贈放在重要位置,及有完善的前線醫護和社區訓練亦是提高器官捐贈率的因素。
不過無可否認的是,數據正告訴我們「默認捐贈」普遍會提升器官捐贈率。外國政府近年都施展渾身解數,在「默認捐贈」外等提供誘因,吸引更多人捐贈器官。
https://hk.thenewslens.com/article/25961
2019年3月27日 星期三
B肝表面抗原陽性的洗腎患者
最近在基層透析的LINE GROUP,看到會員發問:
患者的B肝檢查結果如下:HBsAg(+),Anti-HBsAb(+),HBV DNA:undetectable,這樣要當作有無B肝感染否?
----
先說結論:當作B肝患者隔離。
----
會員們提供的佐證參考資料相當有價值,因此特別記錄下來
1)
The Many Faces of Positive Hepatitis B Surface Antigen
Hepatology. 2016 Oct; 64(4): 1379–1381.
https://aasldpubs.onlinelibrary.wiley.com/doi/full/10.1002/hep.28503
50歲的女性患者要開primary hyperparathyroidism,術前檢查發現如下:
開完parathyroid adenoma後7週,這HBsAg才轉為陰性。
作者認為可能原因是:Therefore, it is highly suspected that the patient's false positive HBsAg was due to heterophilic interference from a paraneoplastic syndrome related to her parathyroid adenoma.
2)
What are the causes and outcomes of the coexistence of HBsAg and anti-HBs?
Braz J Infect Dis vol.20 no.3 Salvador May./June 2016
http://www.scielo.br/pdf/bjid/v20n3/1413-8670-bjid-20-3-0318.pdf
可能原因:
1. mutations in S gene region, particularly in the ‘a’ determinant.
2. the presence of heterologous subtype-specific antibodies,
3. superinfection with a new (second) hepatitis B virus (HBV) strain,
4. occult HBV reactivation
5. false positivity for anti-HBs (False positivity for anti-HBs may be caused by glycoproteins such as pili fractions isolated from Neiserria gonorrhoeae and Escherichia coli.)
3)
The Interpretation of Diagnostic Blood Tests for Hepatitis B Virus (HBV)
Micropathology Ltd
University of Warwick Science Park, Venture Centre, Sir William Lyons Road, Coventry
# HBV DNA - • May be NOT DETECTED in blood but DETECTABLE in the liver
# Phases of HBV infection: Phase 3: inactive-phase
HBsAg loss and seroconversion to HBsAb may occur spontaneously in ~1.5% of cases per year, usually following several years of undetectable HBV DNA. Patients remain infectious but at a lower level.
4)
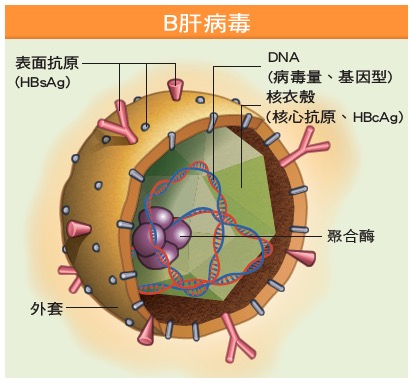
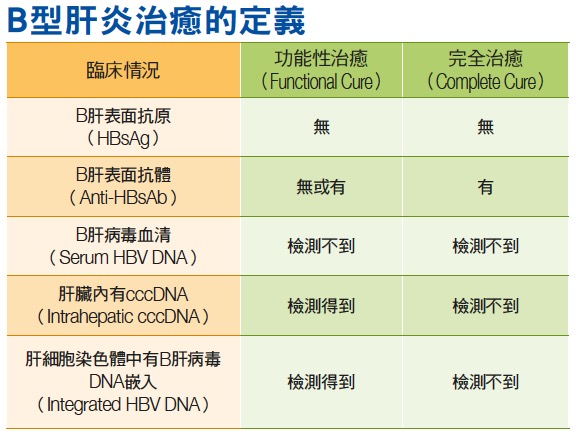
患者的B型肝炎表面抗原消失,但是體內還有具有複製能力的cccDNA存在的情況,被稱為功能性治癒、而非完全治癒。當他們因病情需要接受很強的免疫抑制劑或化療時,比如淋巴癌患者接受化療及莫須瘤(rituximab)治療時,會清除體內大部分的B細胞,統計約有10~15%的人可能因此導致B肝復發,嚴重者甚至出現猛爆型肝炎。因此,這類功能性治癒的B肝患者,雖然血液檢驗看起來不是帶原者,但是當免疫力被抑制時,cccDNA就會再度活化,讓B肝病毒又被製造出來。
財團法人肝病防治學術基金會
https://www.liver.org.tw/newsView.php?cat=3&sid=164
5)

在HBsAg (-) 患者,HBV DNA 占 (+) 57.5%
Investigation of HBV DNA in HBsAg positive patients
Medicine Science 2017;6(4):706-9
https://www.ejmanager.com/mnstemps/53/53-1493293011.pdf?t=1553739690
6)
目前專家意見: B肝分區依據宜以 HBsAg 為準
B肝病毒會嵌入肝細胞核之染色體中,即使血中測不到病毒,日後也可能伺機而動。而C肝病毒是在細胞質、不會進入細胞核中,故容易消滅。


患者的B肝檢查結果如下:HBsAg(+),Anti-HBsAb(+),HBV DNA:undetectable,這樣要當作有無B肝感染否?
----
先說結論:當作B肝患者隔離。
----
會員們提供的佐證參考資料相當有價值,因此特別記錄下來
1)
The Many Faces of Positive Hepatitis B Surface Antigen
Hepatology. 2016 Oct; 64(4): 1379–1381.
https://aasldpubs.onlinelibrary.wiley.com/doi/full/10.1002/hep.28503
50歲的女性患者要開primary hyperparathyroidism,術前檢查發現如下:
Results of our patient's hepatitis B testing
| Test* | HBsAg** | S/CO*** Ratio | Neutralization Test Result | HBcAb | HBeAg | HBeAb | HBsAb | HBV DNA |
|---|---|---|---|---|---|---|---|---|
| 1 | positive | 3.13 (average 3.07) | non-confirmable | negative | not detected | |||
| 2 | positive | 9.24 | no confirmation necessary | |||||
| 3 | positive | 9.70 | no confirmation necessary | |||||
作者認為可能原因是:Therefore, it is highly suspected that the patient's false positive HBsAg was due to heterophilic interference from a paraneoplastic syndrome related to her parathyroid adenoma.
2)
What are the causes and outcomes of the coexistence of HBsAg and anti-HBs?
Braz J Infect Dis vol.20 no.3 Salvador May./June 2016
http://www.scielo.br/pdf/bjid/v20n3/1413-8670-bjid-20-3-0318.pdf
可能原因:
1. mutations in S gene region, particularly in the ‘a’ determinant.
2. the presence of heterologous subtype-specific antibodies,
3. superinfection with a new (second) hepatitis B virus (HBV) strain,
4. occult HBV reactivation
5. false positivity for anti-HBs (False positivity for anti-HBs may be caused by glycoproteins such as pili fractions isolated from Neiserria gonorrhoeae and Escherichia coli.)
3)
The Interpretation of Diagnostic Blood Tests for Hepatitis B Virus (HBV)
Micropathology Ltd
University of Warwick Science Park, Venture Centre, Sir William Lyons Road, Coventry
# HBV DNA - • May be NOT DETECTED in blood but DETECTABLE in the liver
# Phases of HBV infection: Phase 3: inactive-phase
HBsAg loss and seroconversion to HBsAb may occur spontaneously in ~1.5% of cases per year, usually following several years of undetectable HBV DNA. Patients remain infectious but at a lower level.
4)
患者的B型肝炎表面抗原消失,但是體內還有具有複製能力的cccDNA存在的情況,被稱為功能性治癒、而非完全治癒。當他們因病情需要接受很強的免疫抑制劑或化療時,比如淋巴癌患者接受化療及莫須瘤(rituximab)治療時,會清除體內大部分的B細胞,統計約有10~15%的人可能因此導致B肝復發,嚴重者甚至出現猛爆型肝炎。因此,這類功能性治癒的B肝患者,雖然血液檢驗看起來不是帶原者,但是當免疫力被抑制時,cccDNA就會再度活化,讓B肝病毒又被製造出來。
財團法人肝病防治學術基金會
https://www.liver.org.tw/newsView.php?cat=3&sid=164
5)

在HBsAg (-) 患者,HBV DNA 占 (+) 57.5%
Investigation of HBV DNA in HBsAg positive patients
Medicine Science 2017;6(4):706-9
https://www.ejmanager.com/mnstemps/53/53-1493293011.pdf?t=1553739690
6)
目前專家意見: B肝分區依據宜以 HBsAg 為準
B肝病毒會嵌入肝細胞核之染色體中,即使血中測不到病毒,日後也可能伺機而動。而C肝病毒是在細胞質、不會進入細胞核中,故容易消滅。

7)


2019年2月11日 星期一
使用beta-blocker有較少的COPD住院率
以往的內科學訓練告訴我,在開beta-blocker時要注意可能有氣喘(asthma or COPD)的患者,因為會惡化疾病。這個丹麥的觀察型研究,卻告訴我們不一樣的結果。
β-Blocker Therapy and Risk of Chronic Obstructive Pulmonary Disease – A Danish Nationwide Study of 1·3 Million Individuals
Published:January 28, 2019 DOI:https://doi.org/10.1016/j.eclinm.2019.01.004
這是丹麥患者登錄系統中,追蹤了30萬位患者使用beta-blocker超過6個月和100萬位使用其他降血壓藥的患者來比較。有使用beta-blocker有較少的COPD住院率 (649 vs. 919 cases per 100,000 person-years,adjusted hazard ratio [HRadjusted] 0·80, 95% CI 0·79–0·82).
在sub-group分析發現:Risk of COPD hospitalization was lowered in the groups treated with β-blockers among patients with ischemic heart disease (0·72, 0·69–0·75), cardiac arrhythmias (0·76, 0·72–0·80), asthma (0·69, 0·61–0·79), hypertension (0·91, 0·86–0·96), and diseases of the pulmonary circulation (pulmonary embolism and cor pulmonale) (0·72, 0·59–0·87).
甚至All-cause mortality和COPD death也是有下降:in the group treated with β-blockers compared to the group treated with any other antihypertensive drugs (0·56, 0·53–0·59).
作者結論:也許我們應該要改變目前的給藥準則,在可能有COPD患者,beta-blocker不一定是絕對不能使用。
β-Blocker Therapy and Risk of Chronic Obstructive Pulmonary Disease – A Danish Nationwide Study of 1·3 Million Individuals
Published:January 28, 2019 DOI:https://doi.org/10.1016/j.eclinm.2019.01.004
這是丹麥患者登錄系統中,追蹤了30萬位患者使用beta-blocker超過6個月和100萬位使用其他降血壓藥的患者來比較。有使用beta-blocker有較少的COPD住院率 (649 vs. 919 cases per 100,000 person-years,adjusted hazard ratio [HRadjusted] 0·80, 95% CI 0·79–0·82).
在sub-group分析發現:Risk of COPD hospitalization was lowered in the groups treated with β-blockers among patients with ischemic heart disease (0·72, 0·69–0·75), cardiac arrhythmias (0·76, 0·72–0·80), asthma (0·69, 0·61–0·79), hypertension (0·91, 0·86–0·96), and diseases of the pulmonary circulation (pulmonary embolism and cor pulmonale) (0·72, 0·59–0·87).
甚至All-cause mortality和COPD death也是有下降:in the group treated with β-blockers compared to the group treated with any other antihypertensive drugs (0·56, 0·53–0·59).
作者結論:也許我們應該要改變目前的給藥準則,在可能有COPD患者,beta-blocker不一定是絕對不能使用。
訂閱:
文章 (Atom)